



Merlintrader Stock Hub · Biotech 2026
Nasdaq: $PRME
Prime Medicine ($PRME): the first in vivo Prime Editing trial is recruiting in Auckland while the PM647 filing window runs to September 30
How Prime Editing differs from other gene-editing tools, what PM577a, PM647 and PM359 must prove, the competitive clock, the partnership economics, the cash runway and the dilution risk that sits between scientific promise and clinical value.
Get every Merlintrader report in real time on Telegram: join @merlintraderpub_com.
Latest News
Primary-source check through September 6, 2026. EDGAR carries nothing from Prime Medicine after the Form 10-Q of August 6, 2026; the two facts added at this check are a conference release and a registry record. No announcement yet on the PM647 IND or CTA, which the company guides to the third quarter of 2026.
The first in vivo Prime Editing trial is registered and recruiting in Auckland
The Phase 1/2 study of PM577a in Wilson disease (sponsor identifier Prime-0201, EudraCT 2025-525034-62) was first posted on August 5, 2026 and its record was updated on September 3, 2026 with overall status Recruiting. Two sites are listed: New Zealand Clinical Research in Grafton, Auckland, recruiting, and ARC Texas Liver Institute in San Antonio, not yet recruiting. The design is open-label, single-group, with 42 participants estimated, adults and adolescents from 12 years of age, one intravenous infusion of LNP-formulated Prime Editors, primary outcome the frequency and severity of treatment-emergent adverse events. The registry gives an estimated start of September 2026, primary completion in November 2028 and study completion in December 2028. Registration and site activation are two of the three confirmations that count for a trial start; the first participant dosed is the third and has not been announced.
Three September appearances: Wells Fargo on the 10th, H.C. Wainwright on the 15th, Morgan Stanley on the 16th
Management will host one-on-one meetings at the Wells Fargo 21st Annual Healthcare Conference on Thursday, September 10, 2026 in Boston, and will hold fireside chats at the H.C. Wainwright 28th Annual Global Investment Conference on Tuesday, September 15, 2026 at 9:30 a.m. ET and at the Morgan Stanley Global Healthcare Conference on Wednesday, September 16, 2026 at 10:00 a.m. ET, both in New York. The two fireside chats are webcast, with replays on the company website for 90 days; the Wells Fargo meetings are not. These are communication events, not data events, but they are the first public occasions since the trial record turned to Recruiting and since the PM647 submission window entered its last month.
$95.1 million of cash and investments, runway “into 2027”, and a going-concern paragraph
Cash and cash equivalents were $47.5 million and short-term investments $47.6 million at June 30, 2026, with a further $13.7 million of restricted cash outside that total. Net cash used in operating activities was $83.8 million in the first half; the quarterly net loss was $42.1 million, research and development $33.4 million and general and administrative $11.0 million. Management states that existing cash, cash equivalents and investments fund operations into 2027, and the same filing concludes that conditions raise substantial doubt about the company’s ability to continue as a going concern within one year of the filing date, because a financing that is not yet committed cannot be counted. The count of common shares was 181,376,856 at July 31, 2026. The release restated the PM647 IND and/or CTA submission for the third quarter of 2026 and initial PM577a data for 2027.
Bull Case vs. Bear Case
The constructive case
The platform has crossed from slides into people twice. PM359 restored NADPH oxidase activity in two chronic granulomatous disease patients in a peer-reviewed report and holds RMAT, Fast Track, Orphan Drug and Rare Pediatric Disease designations. PM577a, the first in vivo Prime Editing therapy, cleared a New Zealand CTA in June and a U.S. IND in July 2026, and its Phase 1/2 trial is registered as NCT07748403 and recruiting at the Auckland site as of the September 3, 2026 registry update. A binding arbitration with Beam Therapeutics ended in July 2026 with no breach and no damages, clearing PM647’s field. The 2025 restructuring cut research and development spending from $41.4 million in the second quarter of 2025 to $33.4 million a year later, and the Bristol Myers Squibb collaboration carries up to $3.5 billion of contingent milestones plus $64.0 million of deferred revenue still to be recognised. If the same LNP and editor stack corrects two liver diseases in 2027, one platform will have produced several assets.
The sceptical case
The balance sheet does not wait for the science. Cash and investments of $95.1 million at June 30, 2026 stand against $83.8 million of operating cash used in six months, the Form 10-Q states substantial doubt about going concern, and the company has a $200 million ATM prospectus and a $500 million shelf ready: a financing before the 2027 data is the base case, and Finviz reports short interest at 36.7% of the float on September 6, 2026. PM577a starts in clinically stable adults on background therapy, where early efficacy is hard to read, and the registry places primary completion in November 2028. PM647 has no human data while BEAM-302 has 29 treated patients and a pivotal plan, and its IND or CTA submission is still a window that closes on September 30, 2026. PM359 rests on two patients and a registry record that runs to 2030. The September conferences are dates; the first participant dosed is not yet one.
Next event with a date
H.C. Wainwright 28th Annual Global Investment Conference, fireside chat — Tuesday, September 15, 2026, 9:30 a.m. ET (15:30 CEST), New York, webcast
Announced on September 3, 2026. Before it, management holds one-on-one meetings at the Wells Fargo 21st Annual Healthcare Conference on Thursday, September 10, 2026 in Boston, which are not webcast; after it, a second fireside chat at the Morgan Stanley Global Healthcare Conference on Wednesday, September 16, 2026 at 10:00 a.m. ET (16:00 CEST). Replays stay on the company website for 90 days. These are the only company events with a published date. The PM647 IND and/or CTA submission remains a third-quarter 2026 window that closes on September 30; the first participant dosed in the PM577a trial, whose registry record turned to Recruiting on September 3, 2026, has no announced date; initial PM577a clinical data are a 2027 window.
At a glance
Reference price — Sept. 4, 2026 close
$3.70
Nasdaq close, September 4, 2026 (Marketstack)
Market cap — Sept. 4, 2026 close
$671.1M
Merlintrader calculation: 181,376,856 shares at July 31, 2026 × $3.70 close of September 4, 2026. Finviz shows $671.09M while its own share field reads 180.74M, the June 30, 2026 count, which does not reproduce that value at the close: the two aggregator fields are reported as given
Cash + investments — June 30, 2026
$95.1M
June 30, 2026; excludes $13.7M restricted cash
H1 2026 operating cash use
$83.8M
Net cash used in operating activities, six months ended June 30
Company runway
Into 2027
Management guidance—not a promise of funding through all 2027
Going concern
Substantial doubt
Management’s explicit ASC 205-40 conclusion in the Q2 10-Q
Lead in vivo trial
PM577a recruiting
NCT07748403 status Recruiting at the September 3, 2026 registry update; Auckland site open, San Antonio not yet
Shares outstanding — July 31, 2026
181.38M
Common shares as of July 31, 2026
No approved productsNo product revenueFirst in vivo data expected 2027Permanent-editing riskFinancing is part of the thesis
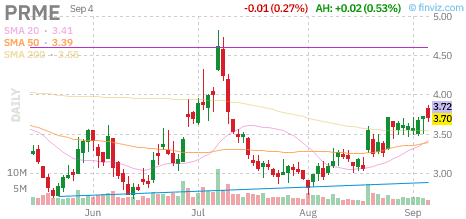
$PRME daily chart, Finviz, through the September 4, 2026 closeSource: Finviz. Informational only; the chart is not a recommendation.
Guided window, not a date
PM647 IND and/or CTA submission guided for Q3 2026, a window that closes on September 30, 2026 with no filing announced at September 6
The submission would place the second liver program behind PM577a and test whether Prime’s “universal” LNP and modular development model can support two disease-specific editors. It remains company guidance until a filing and clearance are announced.
The debate in one line
Prime has real human proof of concept, but only in two PM359 patients—and the balance sheet may require financing before the larger in vivo thesis is clinically validated
The scientific reach is broad: one platform, several mutation types. The investable question is narrower: can Prime translate that breadth into reproducible human data before dilution, program complexity and better-funded competitors compress its strategic options?
01 Executive summary and investor readout
Prime Medicine is trying to turn “search-and-replace” genome editing into a therapeutic platform. Its Prime Editors are designed to rewrite a targeted DNA sequence without intentionally creating a double-strand break and without requiring a separate donor-DNA template. In theory, that architecture can address substitutions, small insertions and small deletions that sit outside the cleanest use cases for nuclease editing or one-letter base editing.
The company is no longer only a preclinical platform story. PM359 produced peer-reviewed proof of concept in two participants with p47phox-deficient chronic granulomatous disease, and the FDA granted RMAT designation. PM577a has cleared an IND in the United States and a CTA in New Zealand, creating Prime’s first authorized in vivo program. PM647 is expected to follow, with regulatory submission guided for the third quarter of 2026.
That progress does not remove the central risks. The PM359 evidence is exceptionally small and uses an ex vivo autologous stem-cell workflow with busulfan conditioning. PM577a and PM647 have not yet reported human data. Prime’s Q2 2026 10-Q says there is substantial doubt about its ability to continue as a going concern for the following twelve months, while management separately guides cash runway “into 2027.” Those statements are not contradictory: runway guidance is an operating estimate; the accounting conclusion reflects the need for additional capital that management cannot consider probable until it is secured.
What may be underappreciated
If the same editor-and-LNP stack produces meaningful human correction in Wilson disease and AATD, Prime would have evidence that one modular platform can create several in vivo assets. That would be more valuable than success in a single indication and could improve partnership leverage.
What may be underestimated
Cash plus investments of $95.1 million is small relative to an $83.8 million six-month operating cash use, even after restructuring. A financing event is not a footnote: its price, timing and size can materially change per-share outcomes before the 2027 clinical readouts.
What is deliberately left out, and why: Prime is scientifically differentiated and has crossed a meaningful human-validation threshold, but the current thesis cannot be separated from capital formation. No price target is presented because any defensible model would be dominated by unsupported assumptions about financing, probability of success, launch timing, pricing and penetration.
02 Prime Editing: what is different—and what is not yet proven
Prime Editing combines a Cas protein adapted to nick DNA with a reverse transcriptase and a prime-editing guide RNA, often called a pegRNA. The pegRNA both directs the machinery to a genomic address and carries the template for the desired rewrite. Rather than cutting both DNA strands, the system nicks the target and copies the programmed sequence into the genome.
The practical attraction is flexibility. A nuclease system is powerful when disrupting a gene or relying on cellular repair is enough. A base editor is efficient for certain single-letter transitions. Prime Editing is designed for a wider menu: all twelve possible base-to-base substitutions in principle, plus targeted small insertions and deletions. That is why the platform is often described as “search and replace,” though the metaphor can sound easier than the biology.
The three-layer execution problem
| Layer | What must work | What can fail |
|---|---|---|
| Editor design | The pegRNA and editor must produce enough correct product at the intended locus. | Low efficiency, byproducts, unintended sequence changes or cell-type variability. |
| Delivery | The editor must reach the relevant cells at a tolerable dose. Prime uses LNP delivery in liver and an ex vivo process for PM359. | Insufficient tissue exposure, immune reactions, liver-enzyme elevations or an impractical dose. |
| Clinical translation | Molecular correction must produce durable patient benefit and a regulator-acceptable benefit-risk profile. | A strong biomarker may not change outcomes; rare toxicities may emerge only in larger or longer follow-up. |
PM359 offers the first direct answer to the editor-design question in humans: edited autologous stem cells engrafted and generated measurable NADPH oxidase activity. It does not answer the in vivo delivery question for liver or lung, and it does not establish long-term safety across a broad population. PM577a and PM647 therefore carry more than asset-specific risk; they test whether Prime Editing can move from an ex vivo manufacturing setting into systemic delivery.
Do not collapse gene-editing categories. Prime Editing, base editing and nuclease editing have overlapping goals but different mechanisms, payloads, efficiency trade-offs and safety questions. A competitor’s success validates the therapeutic concept of permanent correction, not Prime’s exact molecule or delivery system.
03 The focused strategy after the 2025 restructuring
In May 2025, Prime narrowed internal investment around two in vivo liver programs—Wilson disease and AATD—reduced its workforce by approximately 25%, and changed leadership. Former CEO Keith Gottesdiener left the chief-executive role; former CFO Allan Reine became CEO, while Jeff Marrazzo, a director since May 2023 and co-founder of Spark Therapeutics, became Executive Chair. The company said the restructuring would reduce cash needs through 2027 by almost half.
The wording matters. “Reduce cash needs” did not mean that existing cash would fund every program through decisive clinical data. It meant fewer parallel internal bets, lower personnel costs and a clearer sequence for deploying capital. Q2 2026 R&D expense fell to $33.4 million from $41.4 million a year earlier, and G&A fell to $11.0 million from $13.1 million. Yet the company still used $83.8 million of cash in operations during the first half of 2026.
PM359 also demonstrates how strategy can evolve. The 2025 plan initially deprioritized the CGD program while Prime sought a partner. After the first two treated patients generated encouraging proof of concept, a peer-reviewed publication and regulatory momentum, Prime re-engaged around a potential BLA path. That is rational if regulators accept a highly tailored evidence package for an ultra-rare, serious disease—but it adds a manufacturing and regulatory workstream to the two liver launches.
What the focused strategy must prove: that lessons from PM577a’s LNP, toxicology, manufacturing and regulatory package meaningfully shorten PM647 development; that PM359 can advance without consuming the capital required for the liver readouts; and that partnered programs can create non-dilutive funding rather than only distant contingent value.
04 PM577a in Wilson disease: the first in vivo Prime Medicine trial
Wilson disease is caused by pathogenic variants in ATP7B, impairing copper transport and allowing toxic copper accumulation, especially in the liver and brain. PM577a is designed for patients with the H1069Q variant. Prime says this is the single most common disease-causing variant in the United States and a major variant in Europe, but the addressable population is narrower than all Wilson disease because genotype eligibility matters.
New Zealand’s Medsafe cleared a CTA in June 2026, and the FDA cleared the U.S. IND in July. Prime describes the planned global Phase 1/2 trial as an open-label, first-in-human, ascending-dose study in adults and adolescents, starting with adults who are clinically stable on standard-of-care therapy. The study is intended to measure safety, tolerability, biological activity and efficacy.
The trial now has a public record. ClinicalTrials.gov NCT07748403, sponsor identifier Prime-0201 and EudraCT number 2025-525034-62, was first posted on August 5, 2026 and updated on September 3, 2026 with overall status Recruiting: New Zealand Clinical Research in Grafton, Auckland, is recruiting and ARC Texas Liver Institute in San Antonio is not yet recruiting. The record lists 42 participants estimated, a minimum age of 12 years, a single intravenous infusion of LNP-formulated Prime Editors, a primary outcome of treatment-emergent adverse events by frequency and severity, an estimated start in September 2026, primary completion in November 2028 and study completion in December 2028. The EudraCT number signals a European component that the two listed sites do not yet show. A separate prescreening study, NCT07226622, started on December 29, 2025 to identify adults carrying H1069Q or R778L, with 30 estimated participants and an estimated completion in December 2027; at the May 12, 2026 registry update its status was active, not recruiting.
What a useful first dataset must show
- Editing exposure: credible evidence that the LNP delivered the Prime Editor into hepatocytes and generated the intended correction.
- Functional biology: movement in copper-related biomarkers that is coherent with restored ATP7B function, not a single noisy measure.
- Safety: manageable infusion reactions and liver-enzyme changes, without a signal that makes redosing or dose escalation impractical.
- Dose logic: a dose-response that supports a development dose rather than a maximum technically deliverable dose.
- Durability: persistence long enough to support a one-time-therapy thesis. Initial 2027 data will necessarily be early.
The starting population creates a difficult interpretation problem. Clinically stable adults are safer for first-in-human development, but background therapy and baseline stability can make early efficacy hard to read. Investors should look for prespecified biomarker definitions, patient-level data and follow-up—not only a company summary that an endpoint “improved.”
Guidance boundary: trial startup in the second half of 2026 and initial data in 2027 are company expectations, not guaranteed dates. IND clearance authorizes a trial; it is not evidence that the therapy is effective or that sites will enroll on schedule.
05 PM647 in AATD: two-sided target biology, unfavorable competitive timing
PM647 is designed to correct the E342K, or PiZ, mutation in SERPINA1. The mutation produces misfolded Z-AAT that accumulates in the liver while leaving too little functional alpha-1 antitrypsin in circulation to protect the lungs. A successful one-time editor therefore has a two-sided objective: reduce toxic Z-AAT and create functional M-AAT.
Prime reported that PM647 restored M-AAT into the healthy human range in fully humanized mouse models at what it calls clinically relevant doses. Those are encouraging company-reported preclinical results, not human efficacy. Prime expects an IND and/or CTA submission in Q3 2026 and initial clinical data in 2027.
A July 2026 binding arbitration resolved a dispute with Beam Therapeutics over the companies’ 2019 agreement. The tribunal determined that PM647 sits within Prime’s defined field, that Prime had not breached the agreement, and that no monetary damages were owed. This removes a material program-specific overhang; it does not remove the normal intellectual-property, freedom-to-operate or competitive risks of a crowded gene-editing field.
BEAM-302 is the benchmark Prime cannot ignore
Beam’s BEAM-302 is already clinical. As of a February 10, 2026 cutoff, Beam had treated 29 patients. In its selected 60 mg cohort, the company reported mean total AAT of 16.1 µM, corrected M-AAT representing 94% of circulating AAT, and an 84% mean reduction in Z-AAT. Beam planned a roughly 50-patient pivotal expansion using biomarkers over 12 months.
Cross-trial comparisons will remain imperfect, especially before PM647 reaches patients. But the sequencing is decisive: PM647 must offer a compelling profile in editing, exposure, safety, dose, manufacturability or patient reach—not merely reproduce a concept Beam has already demonstrated in humans. Prime’s possible advantage is a flexible rewrite rather than a one-letter conversion; its burden is to prove that extra molecular machinery can be delivered efficiently enough.
Competitive read-through: BEAM-302’s human data reduce biological uncertainty around correcting PiZ in vivo, which is helpful for the field. They simultaneously raise the commercial and clinical bar for PM647. Validation and competition can be true at the same time.
06 PM359 in CGD: real human proof, extremely small evidence base
PM359 is an autologous CD34+ hematopoietic stem-cell product for p47phox-deficient chronic granulomatous disease caused by mutations in NCF1. Cells are collected from the patient, edited ex vivo using an all-RNA Prime Editor, released after manufacturing tests and returned after myeloablative busulfan conditioning.
The peer-reviewed report in The New England Journal of Medicine described two treated participants. Both achieved neutrophil and platelet engraftment. NADPH oxidase activity appeared within one month and was maintained for six months in the first participant and four months in the second at the respective last follow-up. Reported adverse events were consistent with busulfan conditioning. The study was funded by Prime Medicine.
This is important proof of concept: a Prime Edited product was manufactured, infused, engrafted and restored a disease-relevant function in humans. It is not proof of durability, broad safety, manufacturing reproducibility or a conventional approval package. Two observations cannot reliably characterize uncommon toxicities, product variability or long-term clonal behavior.
The public registry, NCT06559176, describes an open-label, single-arm Phase 1/2 study with 12 planned participants, actual start October 17, 2024 and limited enrollment by invitation. The record lists an estimated primary completion in January 2030. Prime nevertheless plans to engage the FDA toward a BLA submission in the first half of 2027.
Why a 2027 BLA path may be possible—but is not assured
PM359 has RMAT, Fast Track, Orphan Drug and Rare Pediatric Disease designations. RMAT can enable intensive FDA interaction and discussion of surrogate or intermediate endpoints, rolling review and priority review eligibility. None of those designations lowers the legal standard for approval or guarantees that two patients are sufficient. The key unknowns are the agreed efficacy threshold, duration of follow-up, number of evaluable patients, manufacturing comparability and post-approval commitments.
Falsifiable checkpoint: before assigning substantial BLA value, look for written company disclosure of the FDA-agreed dataset, required follow-up, manufacturing plan and submission contents. “Working toward a BLA” describes intent; it is not a regulatory agreement to accept the current evidence.
07 Cystic fibrosis, BMS CAR-T and the value outside the three leads
Cystic fibrosis
Prime is developing an in vivo cystic-fibrosis program supported by the Cystic Fibrosis Foundation under two agreements: up to $15.0 million from January 2024 and up to $24.0 million more from July 2025, the latter in two equal tranches of which the first combined $6.0 million of cash funding with a $6.0 million equity investment in the August 2025 offering, the second tied to scientific milestones not yet reached. The June 30, 2026 balance sheet carries an $18.0 million research and development funding liability towards the Foundation. CF showcases Prime Editing’s theoretical strength: disease-causing variants span many sequence types, so a flexible rewrite platform could address mutations that are not served by one editor. It also exposes the platform’s hardest delivery problem. Reaching enough relevant airway cells, overcoming mucus and immune barriers, and achieving durable editing remain formidable tasks.
Until Prime nominates a development candidate, provides a regulator-ready delivery package and discloses human timing, this program should be treated as platform option value—not a core near-term valuation pillar.
Bristol Myers Squibb collaboration and PASSIGE
Prime’s September 2024 collaboration with Bristol Myers Squibb covers Prime Edited ex vivo T-cell products using PASSIGE, a system intended to combine Prime Editing with site-specific integration of larger genetic cargo. The agreement included $55 million upfront and a $55 million equity investment. Prime may be eligible for more than $3.5 billion in preclinical, development and commercialization milestones plus royalties.
The headline milestone figure is contingent, program-dependent and spread across years. It is not cash on the balance sheet and should not be capitalized at face value. The more useful indicators are collaboration revenue, program advancement, option exercises, milestone receipts and BMS’s willingness to keep funding the work. At June 30, Prime carried approximately $64.0 million of current and long-term deferred revenue tied to the collaboration, reflecting performance obligations not yet fully satisfied.
Platform test: a productive BMS collaboration would validate Prime’s ability to serve as an enabling technology partner outside wholly owned rare-disease assets. A quiet partnership with no visible program transitions would leave much of the $3.5 billion headline theoretical.
08 Financial position: runway language versus accounting reality
| Q2 / June 30, 2026 item | Amount | Investor interpretation |
|---|---|---|
| Cash | $47.5M | Immediately liquid operating resource. |
| Short-term investments | $47.6M | Brings unrestricted cash plus investments to $95.1M. |
| Restricted cash | $13.7M | Included in the company’s $108.8M headline but not equivalent to freely deployable cash. |
| Q2 collaboration revenue | $1.2M | Not product revenue; related to the BMS collaboration. |
| Q2 R&D / G&A | $33.4M / $11.0M | Costs fell year over year but remain large relative to available liquidity. |
| Q2 net loss | $42.1M | Basic and diluted loss was $0.24 per share. |
| H1 operating cash use | $83.8M | A backward-looking cash-flow measure, not a precise forecast of future burn. |
| Total liabilities | $209.2M | Includes lease liabilities, deferred revenue and the $18.0M funding liability towards the Cystic Fibrosis Foundation; it is not all financial debt. |
| Stockholders’ equity | $39.8M | Down from $120.9M at year-end 2025 as losses accumulated. |
Management says existing cash, cash equivalents and investments should fund operating and capital needs “into 2027.” That phrase does not specify a quarter and does not mean through the 2027 readouts. It also excludes restricted cash from the funds explicitly named in the guidance sentence, even though restricted cash appears in the company’s broader liquidity headline.
The 10-Q separately states that conditions raise substantial doubt about Prime’s ability to continue as a going concern for twelve months after the financial statements were issued. Accounting rules prevent management from treating a future financing as probable when it is not committed and controlled by the company. The resulting message is clear: Prime expects to operate into 2027, but it does not currently have secured resources sufficient to remove financing doubt over the accounting horizon.
Practical conclusion: an investor who models only the $108.8 million headline and the words “into 2027” is missing the strongest disclosure in the filing. The going-concern paragraph makes external capital, a partnership payment, cost reductions or some combination a central 2026–2027 variable.
US$ millions, as filed. The fourth quarter of 2025 is the arithmetic residual of the full-year and nine-month figures.
$40.6MQ1 2025
$41.4MQ2 2025
$44.0MQ3 2025
$34.7MQ4 2025
$34.1MQ1 2026
$33.4MQ2 2026
09 Capital structure and dilution map
Prime reported 181,376,856 common shares outstanding as of July 31, 2026. The diluted economic count is higher. At June 30, the company excluded approximately 26.0 million potential shares from diluted EPS because the business was loss-making: about 22.5 million option shares and 3.5 million unvested performance awards. Time-based options outstanding totaled approximately 21.7 million at a weighted-average exercise price of $3.60.
The company also has broad equity-issuance infrastructure. A 2023 at-the-market program permits sales of up to $300 million. A shelf registration filed on November 7, 2025 and declared effective on March 4, 2026 covers up to $500 million of securities; the current ATM prospectus covers up to $200 million, while an additional $100 million would require another prospectus supplement. The H1 2026 cash-flow statement and relatively stable share count do not indicate meaningful ATM usage during that period, but unused capacity is precisely what gives the company flexibility to sell shares later.
How dilution should be analyzed
- Amount: capital raised relative to the roughly $671 million equity value at the September 4, 2026 close, a Merlintrader calculation.
- Price: shares sold near or below the current price create more dilution than the same proceeds after strong data.
- Timing: raising before PM577a or PM647 data protects the runway but transfers more upside to new capital; waiting increases financing risk.
- Use of proceeds: funding two liver trials and a defined PM359 filing package is different from reopening a broad discovery portfolio.
- Non-dilutive offsets: BMS or other partnership receipts matter only when achieved, not when listed as headline potential.
Dilution is not automatically thesis-breaking. A well-priced raise that funds decisive data can increase enterprise value even as the share count rises. The danger is serial low-price issuance without enough clinical progress to improve the company’s bargaining position.
10 Ownership, management and governance
The 2026 proxy provides a dated ownership snapshot as of March 31. Co-founder David Liu was reported at 20.3 million shares, or 11.26%; ARCH at 18.5 million, or 10.24%; GV at 16.6 million, or 9.17%; and Bristol Myers Squibb at 11.0 million, or 6.09%. Executive officers and directors as a group were shown at approximately 29.0 million shares, or 16.04%, with Robert Nelsen’s interest overlapping ARCH.
These figures can change and beneficial-ownership rules can aggregate shares differently from a simple common-share count. Their relevance is strategic: Prime has a scientifically influential founder, long-term venture holders and a pharmaceutical partner as meaningful owners. That can support patience through development, but it does not eliminate financing dilution or ensure that all holders have the same time horizon as public-market investors.
CEO Allan Reine combines finance and operating experience; Svetlana Makhni has been chief financial officer since April 16, 2026 (Form 8-K of the same date). Reine and is now responsible for converting a founder-era platform into a focused clinical company. Executive Chair Jeff Marrazzo remains a key strategic figure. The governance test over the next year is capital allocation: maintain two in vivo launches, define a credible PM359 BLA package, manage partnerships and finance the business without rebuilding the cost base too quickly.
Management scorecard: on-time PM577a activation, PM647 filing/clearance, transparent FDA communication on PM359, controlled quarterly cash use, and financing terms that extend beyond initial 2027 data.
Beneficial ownership as of March 31, 2026, as reported by the company in its 2026 proxy statement.
36.8%
Four named holders
- David Liu, co-founder20.3 million shares.11.26%
- ARCH Venture Partners18.5 million shares.10.24%
- GV16.6 million shares.9.17%
- Bristol Myers Squibb11.0 million shares, from the 2024 collaboration equity investment.6.09%
- Everyone elseThe residual, a Merlintrader calculation: 100 less the four reported holders.63.24%
11 Competition: program-by-program, not platform-by-slogan
| Prime program | Key comparator | Relative position | What matters |
|---|---|---|---|
| PM577a / Wilson disease | Ultragenyx UX701 and existing chronic therapy | PM577a is authorized to start Phase 1/2; UX701 is in an ongoing Phase 1/2/3 pivotal-stage program. | Genotype reach, copper biology, dose, durability and whether editing improves the standard-of-care burden. |
| PM647 / AATD | Beam BEAM-302 | PM647 is preclinical/IND-enabling; BEAM-302 has 29 treated patients and a pivotal expansion plan. | M-AAT restoration, Z-AAT reduction, safety, dose and time to pivotal evidence. |
| PM359 / p47-CGD | Allogeneic transplant, chronic anti-infective management and other gene-therapy approaches | Peer-reviewed two-patient proof of concept; potential accelerated regulatory discussion. | Durability, manufacturing consistency, conditioning burden, infection outcomes and FDA-required dataset. |
| CF program | Highly effective CFTR modulators and multiple genetic-delivery programs | Early platform program without a disclosed clinical candidate. | Airway delivery, eligible mutations, benefit beyond modulators and repeatability. |
A common analytical mistake is to value Prime against every gene-editing company at the platform level. Patients, investigators and regulators evaluate products. The relevant competitor for PM647 is not “CRISPR” as a category; it is a treatment such as BEAM-302 that targets the same mutation and has already established a human biomarker profile. The relevant competitor for PM577a includes both investigational gene therapy and therapies that already control copper in many patients.
Prime’s strongest strategic response is modular execution: reuse a liver LNP, common manufacturing capabilities and related regulatory knowledge while changing the editor. If that reuse materially shortens timelines and lowers cost, the platform earns economic meaning. If every asset requires a bespoke multi-year solution, breadth becomes a resource burden.
See the Beam Therapeutics Stock Hub for the full BEAM-302 benchmark and the Intellia Therapeutics Stock Hub for a broader in vivo gene-editing comparison.
12 Catalyst calendar and evidence hierarchy
| Window | Potential event | Status at cut-off | What would count as confirmation |
|---|---|---|---|
| Q3 2026 | PM647 IND and/or CTA submission | Company guidance | A dated submission announcement, followed by regulator clearance. |
| Sept. 10, 15 and 16, 2026 | Wells Fargo one-on-ones (Boston); H.C. Wainwright fireside chat 9:30 a.m. ET and Morgan Stanley fireside chat 10:00 a.m. ET (New York) | Announced September 3, 2026; the two fireside chats are webcast | Communication events; a filing or dosing announcement would be the confirmation that matters. |
| H2 2026 | PM577a global Phase 1/2 startup | NCT07748403 registered August 5, 2026 and Recruiting at the Auckland site as of the September 3, 2026 update; San Antonio not yet recruiting | Trial registration/site activation and first participant dosed. |
| 2026–H1 2027 | PM359 FDA dialogue and BLA preparation | RMAT granted; BLA targeted for H1 2027 | Disclosure of agreed evidence/follow-up and actual submission acceptance. |
| 2027 | Initial PM577a clinical data | Company guidance | Patient-level safety, editing/biology, dose and follow-up. |
| 2027 | Initial PM647 clinical data | Company guidance, dependent on filing and trial execution | Human M-AAT/Z-AAT response, safety, dose and durability. |
| Any quarter | Financing or partnership transaction | Likely strategic need, not scheduled | Proceeds, price, warrants, covenants, runway and use of funds. |
Evidence hierarchy
- Regulatory clearance or filing: confirms permission or submission, not efficacy.
- Patient-level clinical data: strongest near-term test, especially with prespecified endpoints and adequate follow-up.
- Peer review: improves transparency but cannot make a two-patient dataset large.
- Preclinical data: useful for mechanism and dose selection, weak for predicting human benefit.
- Management timelines: relevant for planning, but forward-looking and vulnerable to site, manufacturing and regulator delays.
13 Bull, base and bear scenarios
Bull case
PM577a starts promptly and produces clean evidence of in vivo correction at a practical dose. PM647 enters the clinic and approaches BEAM-302 on functional biology with a competitive profile. FDA feedback supports a defined PM359 BLA package. Prime finances from strength or secures a meaningful partnership, giving the platform runway beyond first data.
Base case
PM577a and PM647 advance, but timelines slip and the first datasets are small. PM359 requires more patients or follow-up than hoped. Scientific optionality remains, yet an equity raise increases the share count before platform value is proven. The stock remains highly catalyst-driven rather than compounding on fundamental revenue.
Bear case
In vivo delivery produces insufficient editing, problematic liver signals or an impractical dose. PM359’s BLA path expands materially. Competitive programs move ahead while Prime raises capital at a depressed price. Management narrows the portfolio again, reducing the platform premium to one or two uncertain assets.
Thesis breakers and disconfirming evidence
- PM577a trial startup moves materially beyond guidance without a clear external reason.
- PM647 cannot reach regulatory clearance or requires a profile inferior to the existing human BEAM-302 benchmark.
- Prime discloses editor-related or delivery-related safety findings that constrain dose or eligible patients.
- The FDA requires a much larger PM359 dataset than the company’s capital plan can comfortably support.
- Quarterly cash use stays near the H1 rate while development timelines extend.
- A financing materially enlarges the share count without funding through decisive clinical evidence.
The thesis should be falsifiable. “Prime Editing can address many mutations” is a platform claim, not an investment conclusion. The conclusion improves only when program-level data, regulatory clarity and funding improve together.
14 Retail sentiment and what not to measure
PRME naturally attracts high-conviction narratives: David Liu’s scientific pedigree, the “search-and-replace” metaphor, the possibility of one-time cures and the comparison with earlier gene-editing winners. The opposite narrative focuses on burn, dilution and the long interval before in vivo data. Both can produce sharp moves around modest news flow.
The block below is the Stocktwits reading at the date shown. Unstructured posts can be useful for identifying questions or crowded expectations, but they are not evidence of clinical probability, institutional positioning or future returns. Treat any trader comments as opinions from non-professional market participants.
15 FAQ
Is Prime Medicine already a clinical-stage company?
Yes. PM359 has treated patients, while PM577a has U.S. IND and New Zealand CTA clearance for a planned global Phase 1/2 trial. PM647 had not yet entered human testing at the September 6, 2026 cut-off, and its IND and/or CTA submission had not been announced.
What is the next most important catalyst?
The nearest dated events are the September 10, 2026 Wells Fargo meetings and the September 15 and 16, 2026 fireside chats; the nearest guided event is the PM647 IND and/or CTA submission in Q3 2026, a window that closes on September 30. The more important value event is human in vivo data from PM577a and later PM647, expected by the company in 2027.
Does RMAT mean PM359 will be approved?
No. RMAT can intensify FDA interaction and enable expedited tools, but it is not approval and does not guarantee that the current dataset is sufficient for a BLA.
Does Prime have cash through the end of 2027?
The company says cash and investments should fund operations “into 2027”; it does not say through year-end. Its 10-Q also reports substantial doubt about going concern over the twelve-month accounting horizon, which makes additional capital a central risk.
Why compare PM647 with BEAM-302?
Both seek to correct the PiZ mutation in AATD and restore functional M-AAT while reducing toxic Z-AAT. BEAM-302 already has human data and is moving toward pivotal development, making it the clearest current benchmark.
Is the BMS deal worth more than $3.5 billion today?
No. That figure represents potential milestones contingent on multiple programs and future achievements. Upfront cash, recognized collaboration revenue and achieved milestones are economically different from headline eligibility.
Primary sources and double-check register
- Prime Medicine Q2 2026 results and business update, August 6, 2026 — program milestones, company timing, quarterly expenses and runway guidance.
- Prime Medicine Form 10-Q for the quarter ended June 30, 2026 — cash, cash flow, shares, going-concern conclusion, ATM/shelf capacity, collaboration accounting and risk factors.
- ClinicalTrials.gov NCT07748403 — PM577a Phase 1/2 record: first posted August 5, 2026, updated September 3, 2026, status Recruiting, sites, enrolment, ages, dates.
- Prime Medicine, September 3, 2026: participation in investor conferences — Wells Fargo September 10, H.C. Wainwright September 15 at 9:30 a.m. ET, Morgan Stanley September 16 at 10:00 a.m. ET.
- ClinicalTrials.gov NCT06559176 — PM359 design, enrollment, status, study dates and sponsor-submitted record.
- New England Journal of Medicine: Prime Editing for p47phox-deficient CGD — peer-reviewed two-participant PM359 report, follow-up and funding disclosure.
- Prime Medicine pipeline — current focus areas, delivery modalities, CF Foundation support and BMS collaboration context.
- Prime Medicine PM359 RMAT announcement, June 22, 2026 — designation and stated regulatory path.
- Prime Medicine strategic restructuring, May 19, 2025 — portfolio focus, leadership change, workforce reduction and cost claims.
- Prime Medicine 2026 proxy statement — dated beneficial ownership, management and governance.
- Beam Therapeutics BEAM-302 clinical update, March 25, 2026 — AATD benchmark, 29-patient safety/biomarker data and pivotal plan.
- ClinicalTrials.gov NCT06389877 — BEAM-302 trial registry.
- Ultragenyx Q2 2026 update and ClinicalTrials.gov NCT04884815 — UX701 Wilson-disease competitive context.
Double-check policy: company pipeline and timing statements were checked against the Q2 10-Q or independent regulatory/trial records where available. PM359 was checked across the company disclosure, ClinicalTrials.gov and the peer-reviewed paper. Competitive statements were checked against competitor releases and trial registries. Future milestones remain guidance. The reference price is the Nasdaq close of September 4, 2026 and the equity value is a Merlintrader calculation on the share count in the Form 10-Q; float, short interest and ownership are Finviz Elite fields pulled on September 6, 2026.
Get these reports in real time
Every Merlintrader stock hub, catalyst update and market brief is published to Telegram the moment it goes live. No paywall, no spam, just the research.
Join @merlintraderpub_com on Telegram
Community: r/MerlintraderPub on Reddit and @merlintraderpub_com on Telegram. Continue the biotech research on the Merlintrader Biotech Stocks Hub.
Editorial and legal disclaimer. This content is for general information and education only. It is not investment research tailored to any person, a solicitation, an offer, or financial, legal, tax or medical advice. Merlintrader does not recommend buying or selling PRME or any security. Biotechnology securities can lose substantial value after clinical, regulatory, manufacturing, financing or commercial events. Permanent gene editing can create risks that emerge only with larger datasets and longer follow-up. Data can change after the stated cut-off. Verify all information with current SEC filings, regulators, trial registries and company disclosures, and consult appropriately authorized professionals before making decisions. Past performance and market-data snapshots do not predict future results.
Merlintrader · Prime Medicine Stock Hub · Evidence cut-off September 6, 2026
Biotech Catalyst Calendar
PDUFA dates, AdCom meetings, clinical readouts and trial completions in one free, filterable calendar.
Open the PDUFA calendar →
PDUFA dates, AdCom meetings, clinical readouts and trial completions in one free, filterable calendar.
Open the PDUFA calendar →